If you have a high Lp(a) and have had a consult with NiaHealth, there's a good chance your NP mentioned a large study we were all waiting on. That study is called Lp(a)HORIZON. On Friday, September 4, the company running it shared the first results.
They were not the results anyone was hoping for. Here's what happened, and what it means for you.
The TLDR: not much changes. But the why is genuinely interesting.
A quick refresher on Lp(a)
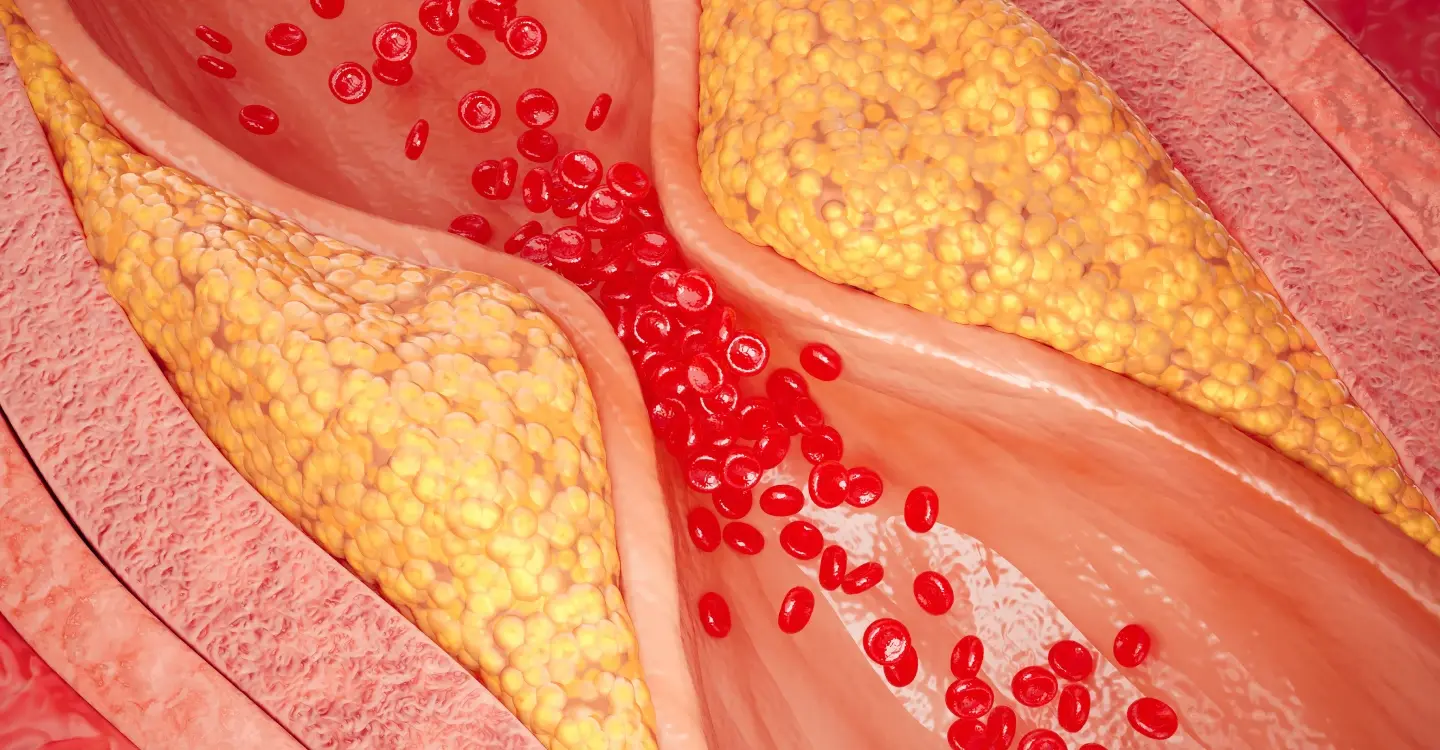
Lp(a) (pronounced "L-P-little-a") is a particle that carries cholesterol through your blood. It's sticky. Over many years, having high Lp(a) levels can accelerate plaque build up inside your arteries, and plaque is what leads to heart attacks and strokes.
The big thing about Lp(a) is that it's roughly 90% set by your genes. You inherit your level from your parents. It barely moves no matter how well you eat, how much you exercise, or how much weight you lose. About 1 in 5 people worldwide has a high level.
When we test your Lp(a), we usually report it in nmol/L (the concentration of particles). A level under 75 nmol/L is generally considered low risk, and a level above roughly 100 nmol/L is where risk starts to climb.
Right now there is no drug designed specifically to lower Lp(a) that has been proven to reduce heart attacks and strokes. That's why the Lp(a)HORIZON trial mattered so much.
What the study tested
Researchers gave an Lp(a)-lowering drug called pelacarsen to 8,323 people who had high Lp(a) and already had heart disease. Everyone in the study had an Lp(a) of at least 150 nmol/L. A separate group with very high levels (at least about 192 nmol/L) was studied on its own. Half got the drug. Half got a placebo (a dummy injection). Everyone kept taking their usual medications for cholesterol and blood pressure.
The results came in two parts:
- The drug did lower Lp(a). That part worked.
- It did not lower the events that actually matter — heart attacks, strokes, deaths from heart disease, and emergency procedures to open a blocked heart artery.
Lowering a number isn't the same as lowering risk
This is one of the trickiest ideas in all of medicine.
We know from a huge amount of research that people born with high Lp(a) get more heart disease than people born with lower levels. So it seemed obvious that pushing Lp(a) down should push risk down too.
But "obvious" and "proven" are different things. Here are a few reasons a drug can move a number without moving the outcome:
- Timing may matter. In most cases, Lp(a) has been contributing to damage in your arteries for decades before heart disease is diagnosed. It's possible that lowering it later in life — after a lot of plaque has already formed — does less than lowering it much earlier would have done. Because the Lp(a)HORIZON trial only enrolled people with heart disease, we can’t say how the drug would have performed in a more preventative scenario.
- There may not be much risk left to remove. Everyone in this study was already on good treatment for cholesterol and blood pressure. When the big risks are already handled, there's less room for another drug to show a benefit.
- The trial may not have run long enough. Participants were followed for approximately four years, which may be too short of a timeframe to see a significant effect from the drug.
- Maybe the link isn't as simple as we thought. People born with high Lp(a) clearly get more heart disease — that part is solid. But a trial like this asks a harder question: if we lower Lp(a) with a drug, do fewer people have heart attacks and strokes? A negative result means that we have to look closer into whether Lp(a) levels tell the full risk story.
This has happened before
Medicine has been fooled more than once by fixating on numbers, not outcomes:
- "Good" cholesterol (HDL-c). For years, higher HDL-c looked protective. Several drugs raised HDL-c impressively. In the big trials, there was no reduction in heart attacks and strokes. Some studies showed possible harm.
- Homocysteine. High levels of this blood marker are tied to heart disease. B vitamins reliably lower it. Large trials of vitamin B use found no drop in heart attacks or strokes.
- Blood sugar. Some older diabetes drugs lowered A1c nicely but didn't reduce the complications associated with high blood sugar — some even made them worse.
And the flip side is just as important: sometimes lowering the number works beautifully. Statins lower LDL-C and ApoB, and reduce heart attacks and strokes in big trials. SGLT-2 inhibitors and GLP-1 medications reduce blood sugar and complications associated with diabetes. That's exactly why we lean on those tools so heavily. The only way to find out which camp a drug falls into is to run the trial, which is why we were watching this one so closely.
What we still don't know
This was a topline announcement, meaning the headline result only. The full data hasn't been released yet and will be presented at a medical conference. We are especially curious about the group with the very highest Lp(a) levels, which was studied separately.
Also, pelacarsen isn't the only drug in this race. At least two other Lp(a)-lowering medications are in large trials right now; those results are still years away.
What this means for you as a NiaHealth member
Your recommendations stay essentially the same.
- Knowing your Lp(a) still matters. A high Lp(a) tells us you carry extra lifetime risk. We recommend testing your Lp(a) at least once in your lifetime, and this has not changed. For women, if you test before menopause, a repeat test after menopause is reasonable, since levels can rise.
- A high Lp(a) still changes how hard we push on everything else. Since we can't easily lower Lp(a) itself, we get more aggressive with the risks we can change: ApoB and LDL, blood pressure, blood sugar, smoking, sleep, activity, and alcohol. Nothing about this study weakens that plan — if anything, it makes those levers more important.
- Tell your family. Lp(a) is inherited. If yours is high, your parents, siblings, and kids should get tested.
- Don't change or stop any medication because of this news. Talk to your health care team first.
And we keep watching. We follow the evidence as it arrives, we tell you what changed, and we tell you when something we were hopeful about didn't pan out. When the full Lp(a)HORIZON data is presented, and when the other trials read out, we'll share what we learn.
A final note on "no treatment"
When we say there's no proven treatment for Lp(a), we mean there's no dedicated drug yet shown to lower Lp(a) and reduce heart attacks and strokes. That's not quite the same as "nothing exists":
- Lipoprotein apheresis — a procedure a bit like dialysis that filters lipoproteins, including Lp(a), out of the blood — is available for select very-high-risk patients. It's intensive, done repeatedly, and reserved for specific situations.
- PCSK9 inhibitors (injectable cholesterol drugs) lower Lp(a) modestly, by roughly 15–30%, but they're used mainly to lower LDL, not as an Lp(a) treatment.
So there are tools that can move Lp(a) in certain cases, but none is a simple, proven, dedicated fix, which is exactly the gap drugs like pelacarsen were hoping to fill.
This post is general education, not personal medical advice. Your NiaHealth NP can walk you through what your own results mean for you.
Our editorial standards & process
At NiaHealth, our mission is to make proactive health possible for all Canadians—by combining science with humanity. We believe that rigorous, evidence-informed health information should never feel out of reach. Every word we publish is intentional. We choose language that empowers rather than overwhelms, clarifies rather than complicates, and respects the lived experiences behind every health question. Learn more here.